In this article
- Why rectal cancer is different
- The operation that changed outcomes
- Chemoradiation and 'watch and wait'
- How low can we go
- What the robot adds in the pelvis
- The temporary ileostomy
- Life after a low join
- Questions to ask
Why rectal cancer is different
The rectum lies in the bony pelvis, wrapped in a fatty envelope (the mesorectum) that carries its lymph nodes, surrounded by the nerves that control the bladder and sexual function, and ending in the sphincter muscles that give continence. Removing the cancer with a clear margin, keeping the nerves, and keeping the sphincter is a three-way balance that colon surgery never has to strike.
The operation that changed outcomes
Total mesorectal excision — removing the rectum and its entire fatty envelope intact, in the anatomical plane, rather than cutting through it — brought local recurrence rates down from around 30% to under 10% when it was introduced in the 1980s. Every modern rectal cancer operation is built on it, and the quality of the specimen is checked by the pathologist and reported.
Chemoradiation and 'watch and wait'
For tumours that are large, close to the margin or close to the sphincter, five weeks of chemoradiotherapy (or a short five-day course) is given first. It shrinks the tumour, lowers recurrence, and sometimes makes a sphincter-saving operation possible where it was not. In a minority of patients the tumour disappears completely on imaging and endoscopy; carefully selected patients can then be watched closely instead of operated on — an option that needs strict follow-up.
How low can we go
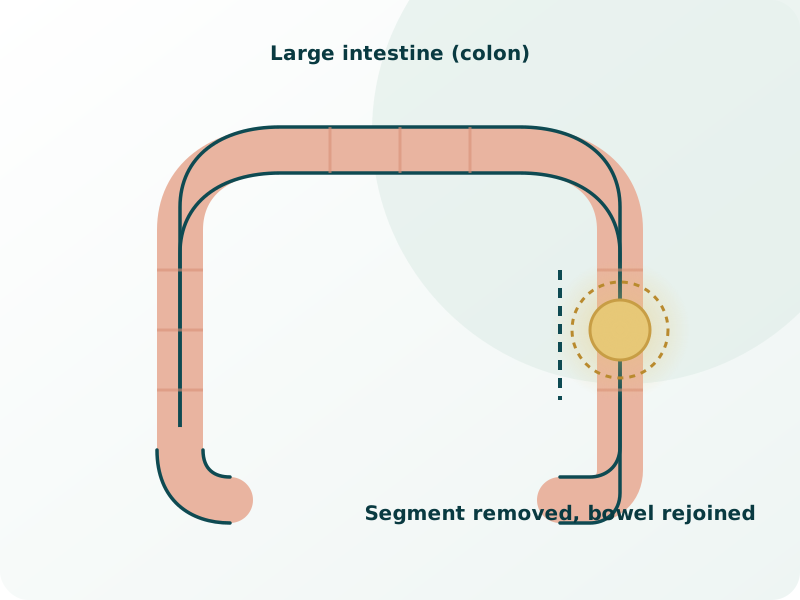
For tumours in the upper and middle rectum, a low anterior resection joins the colon to the remaining rectum. For tumours in the lower rectum, an ultra-low join or an intersphincteric resection — removing part of the internal sphincter — can still avoid a permanent stoma in most patients. Only tumours that have invaded the sphincter muscle itself require an abdominoperineal resection with a permanent colostomy.
What the robot adds in the pelvis
The pelvis is a narrow, deep cone — hardest in men and in patients who are overweight. Straight laparoscopic instruments struggle at its bottom; the robot's wristed instruments and stable, magnified 3D view do not. The ROLARR trial found that robotic surgery reduced conversion to open surgery in exactly these difficult patients — men and the obese — and most surgeons who do both find nerve preservation and the low join easier robotically.
The temporary ileostomy
When the join is very low, a temporary loop ileostomy is made to divert stool away from it while it heals. It is reversed in a short operation after eight to twelve weeks, once a contrast test confirms the join has healed. It is a nuisance, not a life sentence — and it prevents the most dangerous complication of low rectal surgery.
Life after a low join
Some patients have urgency and frequent small stools for months after a very low anastomosis (low anterior resection syndrome). It improves over six to twelve months with diet, fibre, pelvic floor exercises and medicines, and Dr Gupta's team follows patients through it. Bladder and sexual function are preserved in the large majority with nerve-sparing technique.
Questions to ask
What is the distance from the tumour to the sphincter? Will I need chemoradiation first? Can my sphincter be saved? Will I have a temporary stoma, and when will it be reversed? Is the surgery robotic, laparoscopic or open, and why? These decide the outcome as much as the diagnosis itself.
Sources
- Heald RJ, Ryall RD. Recurrence and survival after total mesorectal excision for rectal cancer. Lancet 1986;1:1479–1482.
- Jayne D, et al. Effect of robotic-assisted vs conventional laparoscopic surgery on risk of conversion to open laparotomy among patients undergoing resection for rectal cancer: the ROLARR randomized clinical trial. JAMA 2017;318:1569–1580.

Dr Manoj Gupta
MBBS, MS, DNB (GI Surgery). Senior Director & Head, Robotic & Laparoscopic GI Surgery, GI Oncology and Liver Transplant, Yatharth Super Speciality Hospital. 20+ years, 500+ liver transplants.
This article is general medical education and does not replace a consultation. Figures quoted are from the sources listed and from typical outcomes at experienced centres; your own numbers depend on your condition.